


Efforts by CMS to reform the 340B Drug Pricing Program aim to decrease financial incentives that place revenue over patients' health outcomes and access to care.
KEY POINTS
- The 340B Drug Pricing Program has expanded beyond its original intent to help safety-net providers care for their underserved populations, resulting in large growth in participation and costs associated with the program.
- The 340B Program may prioritize spread, or the margin between the discounted 340B price versus the reimbursement rate received by the covered entity, over patient needs.
- At present, the outsized revenue from drugs purchased through the 340B Program may incentivize consolidation and anticompetitive behavior in the health care market, which has negative implications for health care affordability.
- An ASPE analysis finds that following the halting of the 2017 CMS rule limiting Medicare Part B reimbursement to average sales price (ASP) -22.5%, inflation-adjusted payments for 340B drugs furnished by non-exempt providers increased by $3.6 billion from 2021-2023 ($7.1 billion to $10.7 billion), driving overall drug payments (from $14.3 billion to $17.6 billion).
- The Centers for Medicare & Medicaid Services’ proposed rule to reimburse drugs acquired through the 340B Program at ASP -33.4% aims to reflect reported acquisition costs and reduce hospitals’ incentives to engage in behavior that is misaligned with clinical best practices and that increases costs for consumers.
PROGRAM HISTORY
The 340B Drug Pricing Program (340B) is a federal drug pricing program created in 1992 that is administered by the Health Resources and Services Administration (HRSA).a Figure 1 provides a timeline of the 340B program since its inception.b 340B is authorized by statute (Section 340B of the Public Health Service Act) and allows qualifying covered entities that treat low-income and uninsured patients to purchase outpatient prescription drugsc from pharmaceutical manufacturers at a discounted price. In particular, HRSA calculates a 340B ceiling price for covered drugs, which manufacturers cannot exceed when charging covered entities. For manufacturers to participate in the Medicaid Drug Rebate Program (MDRP) and gain subsequent access to the Medicaid, Medicare Part B, and Veterans Affairs markets, they must participate in 340B.d
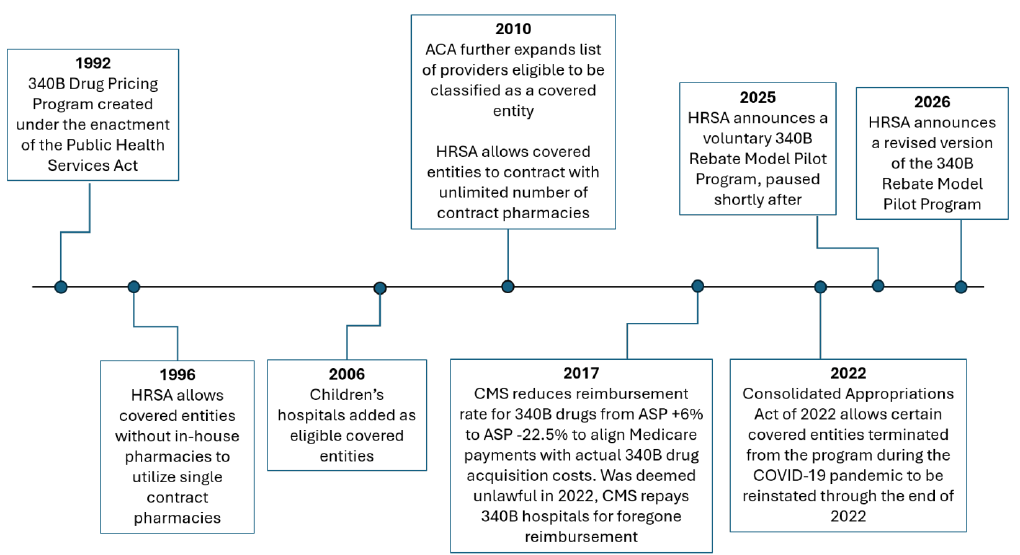
Note: The Consolidated Appropriations Act of 2022 allowed 53 covered entities terminated from the program during the COVID-19 pandemic to be reinstated through the end of 2022.e
340B’s original intent was to help safety-net providers stretch their financial resources further in the delivery of services to their financially vulnerable patients. Reflecting this, initial covered entities were comprised of providers such as disproportionate share hospitals (DSH),f federally qualified health centers (FQHC), and certain specialized clinics and programs.g By allowing covered entities to purchase discounted outpatient prescription drugs but bill commercial insurers and Medicare at standard reimbursement rates, they are able to generate additional revenue that could be used to expand care for their low-income and/or uninsured patients.1
In addition to helping safety-net providers stretch their financial resources, 340B also acted as a “quick fix” for the unintended consequences of the MDRP.2 In its initial operation, the MDRP entitled state Medicaid agencies to the larger of a percentage discount off average prices paid by commercial payers, or the “best price” in the market. This lowered Medicaid programs’ costs, but because the MDRP increased the volume of said best price purchases from 0.1 percent to 10 percent of the market, drug manufacturers increased the “best prices” they offered the original core safety-net providersh to avoid extending the deep discounts they had received to the Medicaid program. 340B aimed to reduce drug prices for these core safety-net providers who had seen the share of drug spending in their fixed budgets increase as a result of the MDRP, which could have impacted their ability to serve patients.
PROGRAM GROWTH
340B has evolved since its enactment, such as expanding provider categories eligible to be a covered entity and allowing contract pharmacies to provide 340B-discounted drugs. As of 2025, there are approximately 66,000 340B covered entities—a large increase from the less than 100 hospitals that initially enrolled in 1993.5
Alongside this large growth in program participation, the costs associated with 340B have increased dramatically as well. In the past decade, 340B drug sales have increased from $12 billion in 2015 to $81 billion in 2024, with majority of the growth coming from hospitals (Figure 2). Among hospitals, DSHs made the most purchases in 2024 at $64.1 billion.3 340B purchases now outpace net Medicare Part B and Medicaid spending on prescription drugs and, among government funded programs, is only surpassed in size by Medicare Part D.4
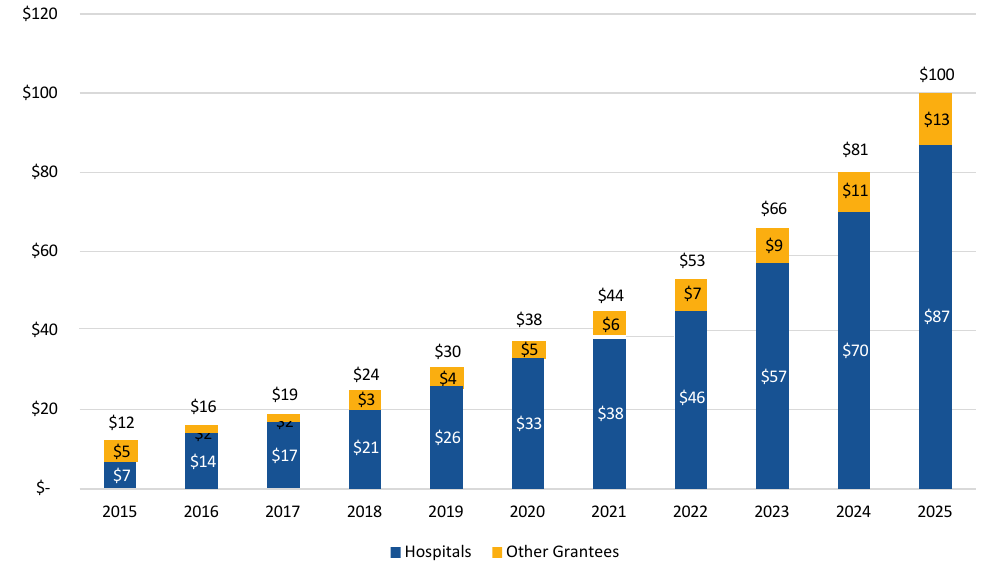
Note: Hospitals include covered entities such as Disproportionate Share Hospitals, children’s hospitals, and critical access hospitals. Other grantees include covered entities such as FQHCs and Ryan White Clinics.
Sources: HRSA 2025 340B Covered Entity Purchases, https://www.hrsa.gov/opa/updates/2025-340b-covered-entity-purchases; Avalere Health, https://advisory.avalerehealth.com/insights/340b-purchase-data-highlights-continued-program-growth-2
PROGRAM IMPLICATIONS
Concerns regarding 340B center on how the program has grown beyond its original intent and the distorted economic incentives of the program. Under the current program structure, hospitals have incentives to prioritize spread—the margin between the discounted price versus the reimbursement rate received by the covered entity—over patient needs and expanding access to low-income and uninsured patients. Additionally, there are concerns that perverse economic incentives may drive the growth in relationships between covered entities and large pharmacy chains, and opportunities for expansion and outsized revenue generation have encouraged engagement in anticompetitive and consolidatory activity.
Financial Spread over Need
340B’s original intent was to give covered entities drug discounts so any revenue from the difference between that cost and standard reimbursement rates could be used to provide services to the low-income and uninsured patients. However, this feature of 340B allows covered entities to leverage spread pricing to generate greater revenue by using higher-priced drugs, increasing drug utilization, and lowering rates of uptake for cheaper generics and biosimilars, all to maximize spread.5 Although FQHCs are required by authorizing statute to reinvest 340B revenue to improve access, expand services, or increase quality of care provided to patients, non-FQHC hospitals, such as DSHs that make up the majority of discounted 340B drug purchases, do not have an equivalent mandate on how they must spend their revenue. Prior research has also revealed differences in service expansion between public and nonprofit hospitals, where 340B participation increased provision of unprofitable services in public hospitals but made no change among nonprofits.6
Spread pricing is also tied to payer mix, as a covered entity’s spread is larger if a patient’s insurer has higher reimbursement rates. This could incentivize covered entities to seek out patients with commercial insurance given its generally much higher reimbursement rates than Medicaid or Medicare. An analysis of 340B net revenue by payer and covered entity type found that 56 percent of hospitals’ revenue was from commercial payers, compared to 32 percent for non-hospital federal grantees.5 In contrast, the majority of federal grantees’ revenue came from Medicaid at 64 percent, compared to 11 percent for hospitals.5 Hospitals, 340B-eligible or not, also had respective price markups that were 6.59 and 4.34 times as high as those in independent physician practices.7 In addition, commercially insured patients are typically responsible for coinsurance and deductible amounts based on the higher reimbursement prices paid by their insurer to the covered entities for drugs that were purchased at 340B discounted prices.
340B-eligible hospital systems can register child sites (e.g., clinics and outpatient treatment centers) that can be located off the hospital’s main campus. While this could be motivated by the covered entities’ desire to best position child site locations for patient access, it could also be to optimize access to patients with commercial insurance to increase spread pricing reimbursement or to strategize competition. One study found that covered entities placed their child sites in wealthier, healthier, and better insured neighborhoods than the area in which the covered entity was located, suggesting an outsized revenue motivation.8 The number of 340B hospital child sites increased from around 7,000 in 2013 to over 34,000 in 2023.8 In 2023, 340B participating DSH spent $7 million more on average on administrative salaries compared to similar non-340B DSH peers.9
Growth in Contract Pharmacies
Another area of concern is the rapid growth in the number of contract pharmacies. Initially, only covered entities without in-house pharmacies were allowed to contract with a pharmacy in order to participate in 340B. In 2010, there were around 1,300 unique contract pharmacies. After covered entities were allowed to contract with multiple pharmacies starting in 2010, this number grew to over 31,000 as of mid-2026.10,i
It is argued that this rapid expansion of contract pharmacies represents revenue seeking misaligned with 340B’s safety-net mission, and in instances where contract pharmacies are used despite their being an available in-house pharmacy, the patients filling prescriptions at the contract pharmacies may have only a tenuous relationship with the covered entity. One study found that while pharmacies that contracted with safety-net clinics were more likely to be in metropolitan areas or areas with higher uninsured rates, their counterparts that contracted with a hospital were more likely to be in lower-poverty areas and less likely to be in medically underserved areas.11
The majority of the growth in contract pharmacy relationships with covered entities is driven by the top five pharmacy chains. Cigna, CVS Health, UnitedHealth Group, Walgreens, and Walmart account for 77 percent of contract pharmacies and are among the largest pharmacies in the country by prescription revenue.10 Contract pharmacies can play an important role in 340B, providing covered entities that do not have in-house pharmacies an opportunity to participate in the program and utilize its discounts. They may also increase patients’ access to medication through convenient pick-up locations. However, contract pharmacies may retain 340B spread when dispensing discounted drugs to insured patients.12 There is also a risk of intentional or unintentional drug diversion, where drugs purchased with 340B discounts under the contract pharmacy arrangement are later dispensed to individuals that are not patients of the covered entity and are therefore ineligible for 340B discounts.13,j Risk of drug diversion is higher in contract pharmacies, as their community role is to dispense medication to patients of covered entities as well as non-covered entities – if medication inventory is not properly maintained, contract pharmacies run the risk of inadvertently dispensing discounted drugs to patients irrespective of their 340B eligibility.
Duplicate Discounts
Duplicate discounts are another area of concern in 340B. State Medicaid agencies are prohibited from seeking Medicaid rebates on drugs purchased at 340B discounted prices. As one means to reduce duplicate discounts, covered entities must inform HRSA upon 340B enrollment that it will use 340B drugs for its Medicaid fee-for-service patients (carve-in) or if it will purchase their drugs through other mechanisms (carve-out).14 State Medicaid agencies are encouraged to follow “best practices” to avoid invoicing manufacturers for drugs purchased at 340B discounted prices.15 One source estimated that one-quarter of total 340B sales represented a duplicate discount of some form across all insurers, covered entities, pharmacies, and patients.16 With the increasing size of the 340B program, duplicate discounts are a key area that requires continuous program integrity efforts.
Consolidation and Rising Prices
The issues with the current structure of 340B discussed above can drive consolidation and anticompetitive behavior in the health care market, which has negative impacts on health care affordability for consumers. There are two types of consolidation; they can occur independently or simultaneously. Horizontal consolidation occurs when entities offering same or similar services merge (e.g., when a health system acquires a hospital, or physician practices providing the same services merge).17 Vertical consolidation occurs when companies at different stages in the care delivery chain merge or come under common ownership (e.g., when a hospital or health system buys physician practices or builds freestanding infusion centers).
The 340B revenue advantage of large covered entities contributes to increased provider concentration and reinforces the market position of already dominant providers. 340B covered entities that merge horizontally or vertically can gain disproportionately large benefits from the program. As hospitals or health systems broaden their footprint through hospital acquisitions or increasing their number of specialty services lines and outpatient facilities, they have the capacity to establish a wider network of 340B child sites and contract pharmacies, allowing them to generate more substantial 340B revenue than smaller hospitals or systems.
Underscoring this issue, a recent study found that 340B participation was associated with almost 50 percent greater total assets compared to similar nonparticipating hospitals.18
Additionally, consolidation that increases market concentration for services also generally increases the prices that commercial insurers pay for all services as it increases providers’ negotiating leverage. There are numerous studies on the effects of consolidation on health care prices, with recent estimates of price increases associated with hospital horizontal mergers ranging from 3.9 to 6 percent, with no clear signal for improvements to care quality.19 Studies have also found that vertical consolidation between physician practices and hospitals is associated with higher commercial prices and outpatient care spending.20 In addition to the greater payment rate leverage that consolidation awards providers, they are also able to charge additional fees (e.g., facility fees) in their new hospital-affiliated settings.21 A 2026 study found that participation in the 340B program reduced transaction prices for clinician-administered drugs only in competitive hospital markets,22 which may reduce out-of-pocket costs for patients in these markets but is unlikely to protect plan members from premium increases related to loss of post-transaction rebates under 340B (see “duplicate discounts”). This underscores that competition plays an important role in decreasing prices, but its intersection with 340B policy shapes the ultimate costs borne by consumers.
Consolidation and concentration also have effects on the amount of federal subsidies that go toward employment-based health insurance and ACA marketplace premiums. If programs like 340B increase commercial insurer premiums, government subsidies such as the ACA’s premium tax credits increase as well to cover the difference. A study found that after adjusting for factors likely to influence premiums, the mean hospital site density accounted for $8.90 of the average Silver benchmark plan’s monthly premium, or subsidies of $106 per year per subsidized ACA enrollee.23 Higher employer health care costs correspond to upward pressure on pre-tax health care premiums and wage stagnation, resulting in lower tax revenue for federal and state governments.24,25,26,27
340B was also found to increase drug costs for self-insured employers, who are responsible for paying claims under their plans.28 To prevent duplicate discounts, manufacturers are typically not required to provide otherwise contractually obligated rebates to these employers when covered entities purchase drugs at the 340B discounted price. By losing manufacturer rebates for drugs purchased through 340B discounts, self-insured employers and their employees may be saddled with a $5.2 billion increase in health care costs—while 340B spread is retained by covered entities.
Impact of Distorted Drug Utilization on Clinical Choices and Patient Outcomes
In oncology, the effects of the 340B program on health care services costs are particularly evident. Because many cancer drugs are high-cost clinician-administered drugs eligible for 340B discounts, hospitals can realize substantial revenue from acquiring oncology practices and converting them into hospital-affiliated sites of care. One study found that among specialties subject to hospital-physician consolidation, oncology had highest rates of growth in vertical integration, increasing to 54 percent in 2017.29 As acquisitions such as these can increase market share and bargaining power of these providers, covered entities have more leverage to negotiate prices with commercial insurers for outpatient drugs. A study of pediatric 340B hospitals found that negotiated prices for newly approved oncology drugs with commercial payers ranged from 102 percent to 630 percent of average sales price (ASP), allowing these covered entities to retain substantial 340B spread.30 Another study found that new 340B participation was associated with higher oncology drug episode spending compared to nonparticipants, with a pronounced increase in episode spending amount among commercial patients.31 Higher spending contributes to increased premiums, deductibles, coinsurance, and other out-of-pocket costs borne by commercially insured patients and their employers.
Motivation for hospitals to increase spread through methods discussed above also has impacts on efficient drug use and outcomes for cancer patients. A study found that participation in 340B moved physician prescribing behavior toward greater use of pharmaceutical treatments for certain cancers typically treated by surgery, radiation, or conservative management alone. Among Medicare beneficiaries, physicians at 340B covered entities increased both their share of patients being treated with cancer drugs as well as their number of pharmaceutical treatments used.32 However, the increase in pharmaceutical usage under 340B was not associated with improved survival for patients with cancer.
PROPOSED RULE
It is argued that the misalignment of Medicare reimbursement and 340B discounted prices plays a role in incentivizing covered entities and contract pharmacies to prioritize spread pricing revenue over patient needs.
Currently, hospitals that receive reimbursement for Medicare Part B drugs under the Medicare Outpatient Prospective Payment System (OPPS) typically receive reimbursement at the ASP +6%. Because covered entities also receive this standard reimbursement rate but purchase drugs at 340B discounted prices, they may be incentivized to use more expensive drugs with higher margins.33
In 2015, the Medicare Payment Advisory Commission estimated that 340B hospitals received an average minimum discount of 22.5% of ASP for drugs paid under the OPPS.34 To better align Medicare reimbursements with the true costs of 340B acquired drugs, CMS issued a rule in 2017, effective beginning in 2018, to change Medicare reimbursement from ASP +6% to ASP -22.5% for Medicare Part B drugs purchased by 340B participating hospitals. However, this payment rate was invalidated by the Supreme Court in June 202235 because HHS had not conducted the statutorily required acquisition-cost survey before varying payment rates among hospital groups. The rate remains ASP +6% to this day.
On April 18, 2025, President Trump signed Executive Order 14273 “Lowering Drug Prices by Once Again Putting Americans First,” which directed the Secretary of Health and Human Services to conduct a survey of outpatient drug acquisition costs, as required by statute, and “consider and propose any appropriate adjustments that would align Medicare payment with the cost of acquisition.”36 Accordingly, CMS conducted this survey of hospitals from January 1 through April 7, 2026. On July 2, 2026, based on the findings from this survey, CMS proposed a rule, which would take effect in 2027 if finalized, for hospitals and most integrated hospital outpatient departments to be reimbursed for drugs acquired through 340B at ASP -33.4% to reflect reported acquisition costs.36 The proposed rule would exempt some types of hospitals, such as children’s and some specialized cancer hospitals. The rule would also establish a uniform payment policy consistent with historic OPPS payment policy of paying the same payment rate for specified covered outpatient drugs (SCODs) and non-SCODs.k
This proposed rule, if finalized, would potentially impact hospital consolidation and the associated costs to patients and the public. The proposed rule would adjust the reimbursement rate to one that more accurately reflects 340B drug acquisition costs, and it would target hospitals’ incentives to engage in many cost-increasing behaviors. With the current reimbursement rate of ASP +6%, hospitals are incentivized to increase their spread by overusing high-cost drugs, seeking Medicare insured patients to increase reimbursement, and drive consolidation through take-up of child sites. In addition to mitigating spread-chasing behaviors that ultimately inflate premiums, reducing the reimbursement rate would also have a direct effect on lowering out-of-pocket costs for Medicare beneficiaries, who under Medicare Part B, typically pay 20 percent of the OPPS reimbursement amount as their coinsurance.
HOSPITAL OUTPATIENT DEPARTMENT 340B SPENDING ANALYSIS
Data and Methods
For our analysis, we present aggregate trends in hospital outpatient department (HOPD) utilization and spending for drugs, overall and stratified by 340B status, using Medicare Outpatient Prospective Payment System (OPPS) claims from 2015 to 2024. The key advantage of this data set is that it provides comprehensive, standardized administrative records for nearly all Medicare fee-for-service hospital outpatient services nationwide. A limitation is that it does not include information on spending among Medicare Advantage enrollees.
Results
Impacts on Hospital Outpatient Drug Payments
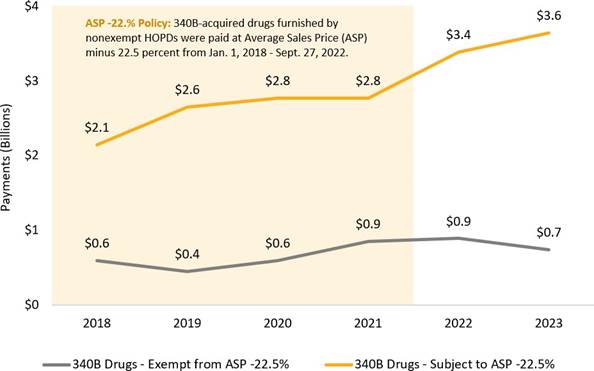
Figure 3 presents overall HOPD drug payments by 340B status before, during, and after the original CMS Medicare OPPS payment rule that limited 340B drug payment to ASP -22.5%. Overall inflation-adjusted drug spending rose each year from 2015 to 2017, increasing 32.5 percent from 2015-2017 or a simple average annual increase of 16.0 percent (Compound Annual Growth Rate (CAGR)=14.9 percent).l When the CMS OPPS rule, finalized in 2017 and effective beginning in 2018, limiting Medicare Part B payments for 340B drugs to ASP -22.5% was in effect for the full calendar years of 2018 through 2021, inflation adjusted payment generally plateaued. Non-340B drug payments, and payments for 340B drugs among exempt providers were flat, and 340B payments to non-exempt provider increased 16 percent from 2018-2019 then remained relatively constant from 2019-2021 ($6.7 billion in 2019 and $7.1 billion in 2021). Inflation-adjusted payments for 340B drugs furnished by non-exempt providers increased by $3.6 billion from 2021-2023 ($7.1 billion to $10.7 billion), increasing at a simple annual growth rate of 25.2 percent (CAGR=22.6 percent).m This increase coincided with a June 2022 Supreme Court ruling that, as determined by a lower court, ultimately required 340B pricing to return to pre-2018 payment rate of ASP +6% by September 2022. The payment increase was driven exclusively by 340B drugs subject to the previous ASP -22.5% rule, providing strong evidence that the rule limited spending increases while in effect.

Notes: HOPDs include both on- and off-campus facilities. In 2024, claims modifier that indicated nonexempt status was being phased out,37 so 340B drug data is presented for all providers in aggregate for that year. On June 15, 2022, the Supreme Court held that CMS could not vary payment rates for outpatient prescription drugs by hospital group, which may have had an anticipatory effect on 340B drug utilization before the September reimbursement change. Payments presented here do not include court ordered retroactive repayments made in 2024 following the overturn of the ASP -22.5% payment policy. Dollar values are inflation adjusted using PCE-Health available from https://meps.ahrq.gov/about_meps/Price_Index.shtml.
Figure 4 shows that drug spending trends relative to 2018 differed drastically after the ASP -22.5% policy was rescinded in 2022, raising the reimbursement rate by 28.5 percentage points (from ASP -22.5% to ASP +6%). For 340B drugs subject to the policy, the amount by which inflation-adjusted payments exceeded the baseline more than tripled from 2021 to 2023 ($3.6 billion increase, from $1.3 billion to $4.9 billion), an increase nearly three times as large as the $1.3 billion increase from 2018 to 2021. In contrast, inflation-adjusted payments for drugs exempt from the policy stayed relatively stable. From 2021 to 2023, inflation-adjusted payments above baseline grew 252 percent for 340B drugs subject to the policy, compared with only 50 percent for 340B exempt drugs. This is strong evidence that restoring the reimbursement rate to ASP +6% increased overall payments. The residual increase in overall payments is due to an increase in the quantity and/or 340B drug mix.n

Notes: HOPDs include both on- and off-campus facilities. On June 15, 2022, the Supreme Court held that CMS could not vary payment rates for outpatient prescription drugs by hospital group, which may have had an anticipatory effect on 340B drug utilization before the September reimbursement change. Payments presented here do not include court ordered retroactive repayments made in 2024 following the overturn of the ASP -22.5% payment policy. Dollar values are inflation adjusted using PCE-Health available from https://meps.ahrq.gov/about_meps/Price_Index.shtml
Figure 5 provides evidence that Medicare Part B reimbursement policy for 340B drugs creates incentives for vertical consolidation. Specifically, there was reduced payment growth among off-campus HOPDs as inflation adjusted payments plateaued during the payment reduction period (2018-2021). Payments only started meaningfully increasing after reimbursement rates increased in 2022. In particular, when the ASP -22.5% policy was lifted in 2022, reimbursements for 340B drugs among off-campus HOPDs increased more sharply despite fewer claims and a similar number of beneficiaries served. By comparison, payments for exempt 340B drugs did not increase, and fell in real dollars. This shows that off-campus HOPDs gain a substantial benefit (approximately $800 million from 2021-2023) when 340B reimbursement by Medicare Part B is more generous, creating the incentive for vertical consolidation among 340B hospitals.
Notes: On June 15, 2022, the Supreme Court held that CMS could not vary payment rates for outpatient prescription drugs by hospital group, which may have had an anticipatory effect on 340B drug utilization before the September reimbursement change. Payments presented here do not include court ordered retroactive repayments made in 2024 following the overturn of the ASP -22.5% payment policy. Dollar values are inflation adjusted using PCE-Health available from https://meps.ahrq.gov/about_meps/Price_Index.shtml
CONCLUSION
The initial goal of the 340B Drug Pricing Program was to help safety-net providers provide better health care and access for underserved populations. However, the program has since expanded beyond this original intent and has instead raised concerns that patient needs are being put second behind financial interests. Covered entities are incentivized to consolidate practices and engage in anticompetitive behavior in order to maximize their spread revenue. Consumers can be harmed by related increases in health care costs and clinical choices that are made to increase revenue over patient outcomes. Reform to Medicare’s OPPS reimbursement policy, if adopted, could better align the incentives of the 340B Program with its original intent.
APPENDIX A
List of Covered Entities under 340B Drug Pricing Programo,38
Federally Qualified Health Centers
- Health center program award recipients
- Health center program look-alikes
- Native Hawaiian health centers
- Tribal and urban Indian health centers
Ryan White HIV/AIDS Program Grantees
Hospitals
- Children's hospitals
- Critical access hospitals
- Disproportionate share hospitals
- Free standing cancer hospitals
- Rural referral centers
- Sole community hospitals
Specialized Clinics
- Black lung clinics
- Comprehensive hemophilia diagnostic treatment centers
- Title X family planning clinics
- Sexually transmitted disease clinics
- Tuberculosis clinics
Chronological Changes to 340B Drug Pricing Program
- 1996: HRSA issued guidance to allow covered entities without in-house pharmacies to use a single external pharmacy, or contract pharmacies.39
- 2006: Children’s hospitals were added as eligible covered entities.
- 2010: The list of providers eligible to be a covered entity was expanded under the ACA to include the following: critical access hospitals, sole community hospitals, rural referral centers, and cancer centers. HRSA also allowed covered entities to contract with an unlimited number of pharmacies to provide 340B-discounted drugs.40,41
- 2017: CMS initially reduces reimbursement rate for 340B drugs from ASP +6% to ASP -22.5% to align Medicare payments with actual 340B drug acquisition costs through a final rule, starting January 1, 2018.42 In 2022, this rule was deemed unlawful by the U.S. Supreme Court due to a procedural error in the policy’s development, and CMS was required to repay 340B hospitals foregone reimbursement for years 2018 through 2022.43
- 2022: The Consolidated Appropriations Act of 2022 allowed certain covered entities terminated from 340B during the COVID-19 pandemic to be reinstated through the end of 2022.44 These covered entities included hospitals eligible for 340B prior to the COVID-19 pandemic but lost their eligibility due to a decrease in their DSH patient percentage during the pandemic.
- 2024: HRSA issued a final rule to establish an administrative dispute resolution (ADR) process (revised from previous final rule of 2020) to resolve claims by covered entities if overcharged for drugs by manufacturers and claims by manufacturers, if an audit finds that a covered entity violated prohibition on diversion or duplicate discounts.45,46,p
- 2025: HRSA announced a voluntary 340B Rebate Model Pilot Program. This program aimed to test the rebate model for drugs on the CMS Medicare Drug Price Negotiation Selected Drug List for 2026, with the goal of better understanding the rebate model’s merits/shortcomings from the perspective of affected stakeholders, and also to shape potential future 340B rebate models that align with the Administration’s goals.47 The program is currently on pause following the US District for the District of Maine’s order in the case American Hospital Association, et al., v. Robert F. Kennedy, et al., with HRSA reconsidering whether to implement a pilot program consistent with its statutory authority.48
- 2026: HRSA posted in the Federal Register a notice regarding the previously paused 340B Rebate Model Pilot Program, announcing the availability of a revised program. This revised program addresses concerns regarding HRSA’s statutory authority over the 340B Program and provides a rebate mechanism through which qualifying manufacturers can effectuate the 340B ceiling price for certain drugs.49
REFERENCES
a The proposed FY2027 President’s Budget integrates the HRSA Office of Pharmacy Affairs into CMS Program Management and allocates $21 million ($8 million above FY2026) to increase oversight of covered entities and drug manufacturers https://www.hhs.gov/sites/default/files/fy-2027-budget-in-brief.pdf↩
b Additional information on the key changes to 340B can be found in Appendix A.↩
c Outpatient drugs covered by 340B include prescription drugs and biologics, other than vaccines. They also include drugs that are delivered via infusion or injection, as long as they are administered in an outpatient setting.↩
d For a manufacturer to get its drugs covered by Medicaid, it is required to provide rebates for a portion of drug payments under the MDRP, upon which Medicaid must cover almost all FDA-approved drugs produced by the manufacturer. In order to access to the benefits that MDRP offers, such as a steady, high volume of patients, manufacturers must be willing to participate in 340B.↩
e For more information about COVID-19 eligibility exceptions see 340B Drug Discount Program: Information about Hospitals That Received an Eligibility Exception as a Result of COVID-19. (2023). U. S. Government Accountability Office. https://www.gao.gov/products/gao-23-106095.↩
f More information on the definition of disproportionate share hospitals can be found here: https://www.cms.gov/medicare/payment/prospective-payment-systems/acute-inpatient-pps/disproportionate-share-hospital-dsh. ↩
g List of the categories of covered entities and changes made throughout the history of 340B can be found in Appendix A.↩
h Core safety-net providers were health care organizations mandated to provide care, regardless of patients’ ability to pay. Providers in this category include clinics funded by the Public Health Service Act and the Department of Veterans Affairs.↩
i It is noted that despite numbers of pharmacy locations decreasing annually since 2022 following some drug manufacturers’ restrictions placed on covered entities distributing 340B drugs via contract pharmacies, the number of contractual relationships has increased.10↩
j The definition of a 340B eligible “patient” can be found here: https://www.hrsa.gov/opa/eligibility-and-registration. Covered entities and contract pharmacies may also engage in vertical integration practices, such as building urgent care clinics, to claim 340B eligibility for patients with whom they do not otherwise have a continuous clinical relationship.↩
k Specified covered outpatient drugs (SCOD) are FDA-approved outpatient drugs in 340B that are subject to a statutory ceiling price and reporting rules, and include brand-name, generic, biologic, and over-the-counter medication.↩
l Calculations based on unrounded dollar amounts.↩
m All calculations are based on unrounded dollar amounts.↩
n For example, as a result of the reimbursement for 340B drugs reverting back to ASP +6%, HOPDs have greater incentive (relative to ASP -22.5%) to start patients on and move patients to drugs with higher reimbursement rates to increase spread revenue.↩
o The list of providers eligible to be a covered entity was expanded in 2010 via the Patient Protection and Affordable Care Act, which included children’s hospitals, cancer treatment facilities, critical access hospitals, rural referral centers, and sole community hospitals that have a certain DSH percentage.↩
p The 2024 final rule is a revised, less formal ADR process as compared to the 2020 final rule. T No claims under the 2020 final rule were adjudicated after HRSA determined the process to be unworkable. https://www.afslaw.com/perspectives/health-care-counsel-blog/new-adr-rule-govern-disputes-between-340b-covered-entities↩
1 Martin, K. (2025, August 6). The 340B Drug Pricing Program: How It Works and Why It’s Controversial. https://doi.org/10.26099/210h-wv98
2 Nikpay, S., Reinke, M., & Quinones, N. (2026). Stretching Scarce Authorizing Legislation as Far as Possible: A Legislative History of the 340B Drug Pricing Program. The Milbank Quarterly. https://doi.org/10.1111/1468-0009.70090
3 2024 340B Covered Entity Purchases. HRSA. (n.d.). Retrieved June 18, 2026, from https://www.hrsa.gov/opa/updates/2024-340b-covered-entity-purchases
4 Kolton Gustafson, Reede, G., & Joldersma, L. (2025, December 22). 340B Purchase Data Highlights Continued Program Growth. Avalere Health Advisory. https://advisory.avalerehealth.com/insights/340b-purchase-data-highlights-continued-program-growth-2
5 Long, R., Karen Mulligan, P., Melissa A. Frasco, P., Erin Trish, P., & Michael E. Chernew, P. USC Leonard D. Schaffer Institute for Public Policy & Government Service (2025). Cui Bono? Misaligned Incentives in the 340B Program. https://doi.org/10.25549/zzrc-6e12
6 Owsley, K. M., Hasnain-Wynia, R., Rooks, R. N., Tung, G. J., Mays, G. P., & Lindrooth, R. C. (2024). US Hospital Service Availability and New 340B Program Participation. JAMA health forum, 5(5), e240833. https://doi.org/10.1001/jamahealthforum.2024.0833
7 Robinson James C., Whaley Christopher, & Dhruva Sanket S. (2024). Hospital Prices for Physician-Administered Drugs for Patients with Private Insurance. New England Journal of Medicine, 390(4), 338–345. https://doi.org/10.1056/NEJMsa2306609
8 Masia, N., Filson, D., Martin, S., & Neumann, U. (2025). Income, health, and racial gaps between 340B hospitals, child sites, and nearby neighborhoods. Health affairs scholar, 3(7), qxaf121. https://doi.org/10.1093/haschl/qxaf121
9 Masia N, Campbell JD, Feyman Y, Finegold K. Association of 340B entity eligibility with changes in hospital financial performance. Health Affairs Scholar. 2026;4(6):qxag147. doi:10.1093/haschl/qxag147
10 Fein, A., & Kapexhiu, G. (2026, June 2). The 340B Contract Pharmacy Market in 2026: A Maturing Industry Dominated by Big Chains and PBMs. Drug Channels. https://www.drugchannels.net/2026/06/the-340b-contract-pharmacy-market-in.html
11 Nikpay, S., Gracia, G., Geressu, H., & Conti, R. (2022). Association of 340B contract pharmacy growth with county-level characteristics. The American journal of managed care, 28(3), 133–136. https://doi.org/10.37765/ajmc.2022.88840
12 Conti, R. M., & Bach, P. B. (2013). Cost Consequences of the 340B Drug Discount Program. JAMA, 309(19), 1995–1996. https://doi.org/10.1001/jama.2013.4156
13 Karen Mulligan, P. (2021). The 340B Drug Pricing Program: Background, Ongoing Challenges and Recent Developments. https://schaeffer.usc.edu/research/the-340b-drug-pricing-program-background-ongoing-challenges-and-recent-developments/
14 Health Resources & Services Administration. (2020, July). Duplicate Discount Prohibition. https://www.hrsa.gov/opa/program-requirements/medicaid-exclusion
15 Centers for Medicare & Medicaid Services, Center for Medicaid and CHIP Services. Best Practices for Avoiding 340B Duplicate Discounts in Medicaid. CMCS Informational Bulletin. January 8, 2020. https://www.medicaid.gov/federal-policy-guidance/downloads/cib010820.pdf
16 Greenwalt, L. (2021, December 20). Uncover the Invisible Impacts of 340B Discounts. IQVIA. https://www.iqvia.com/locations/united-states/blogs/2021/12/uncover-the-invisible-impacts-of-340b-discounts
17 Levinson, Z., Hulver, S., Godwin, J., & Neuman, T. (2025, February 19). Key Facts About Hospitals. KFF.
18 Masia N, Campbell JD, Feyman Y, Finegold K. Association of 340B entity eligibility with changes in hospital financial performance. Health Affairs Scholar. 2026;4(6):qxag147. doi:10.1093/haschl/qxag147
19 Environmental Scan on Consolidation Trends and Impacts in Health Care Markets. (2022). Office of the Assistant Secretary for Planning and Evaluation. https://aspe.hhs.gov/reports/environmental-scan-consolidation-health-care-markets
20 Neprash, H. T., Chernew, M. E., Hicks, A. L., Gibson, T., & McWilliams, J. M. (2015). Association of Financial Integration Between Physicians and Hospitals With Commercial Health Care Prices. JAMA Internal Medicine, 175(12), 1932–1939. https://doi.org/10.1001/jamainternmed.2015.4610
21 Congressional Budget Office. (2022, January 20). The Prices That Commercial Health Insurers and Medicare Pay for Hospitals’ and Physicians’ Services. https://www.cbo.gov/publication/57422
22 Desai, S. M., Padmanabhan, P., Smith, K., Chang, J., & McWilliams, J. M. (2026). The 340B Drug Pricing Program, Hospital Prices, and Competition in Commercial Markets. Health services research, 61(1), e70085. https://doi.org/10.1111/1475-6773.70085
23 Masia, N., Motyka, J. D., Westrich, K., & Campbell, J. D. (2025). The Association of the 340B Program with Affordable Care Act (ACA) Premiums: A Longitudinal Analysis from 2018 to 2022. Inquiry : a journal of medical care organization, provision and financing, 62, 469580251370317. https://doi.org/10.1177/00469580251370317
24 Hager KD, Mozaffarian D, Emanuel EJ, Herring B, Lentz LK, et al. Employer-sponsored health insurance premium cost growth and the distribution of wages, 1988–2019. JAMA Netw Open. 2024;7(1).
25 Abel, J. R., Deitz, R., & Montalbano, N. (2026). Are Rising Employee Health Insurance Costs Dampening Wage Growth?
Liberty Street Economics. https://doi.org/10.59576/lse.20260304b
26 Blanton, K. (2025, April 10). Workers Drop Health Insurance, Stabilizing Employer Costs. Center for Retirement Research at Boston College. https://crr.bc.edu/workers-drop-health-insurance-stabilizing-employer-costs/
27 Burtless, G., & Milusheva, S. (2012, May 9). Effects of Employer Health Costs on the Trend and Distribution of Social-Security-Taxable Wages. Brookings. https://www.brookings.edu/articles/effects-of-employer-health-costs-on-the-trend-and-distribution-of-social-security-taxable-wages/
28 Sun, C., Zeng, S., & Martin, R. (2024). The Cost of the 340B Program Part 1: Self-Insured Employers. IQVIA. https://www.iqvia.com/locations/united-states/library/white-papers/the-cost-of-the-340b-program-part-1-self-insured-employers
29 Nikpay, S. S., Richards, M. R., & Penson, D. (2018). Hospital-Physician Consolidation Accelerated In The Past Decade In Cardiology, Oncology. Health Affairs, 37(7), 1123–1127. https://doi.org/10.1377/hlthaff.2017.1520
30 Liu, I. T. T., Wang, J., Sarpatwari, A., Kesselheim, A. S., & Feldman, W. B. (2024). Commercial markups on pediatric oncology drugs at 340B pediatric hospitals. Pediatric Blood & Cancer, 71(9), e31158. https://doi.org/10.1002/pbc.31158
31 Chang, J., Karaca-Mandic, P., Nikpay, S., & Jeffery, M. M. (2023). Association Between New 340B Program Participation and Commercial Insurance Spending on Outpatient Biologic Oncology Drugs. JAMA Health Forum, 4(6), e231485–e231485. https://doi.org/10.1001/jamahealthforum.2023.1485
32 Horn, D. (2025). The incentive to treat: Physician agency and the expansion of the 340B drug pricing program. Journal of Health Economics, 101, 102971. https://doi.org/10.1016/j.jhealeco.2025.102971
33 Graham, J. R. (2026, April 22). The Hospital Cost Crisis: How Government Policies Drive Consolidation, Undermine Competition, and Fuel Soaring Prices. Paragon Health Institute. https://paragoninstitute.org/private-health/the-hospital-cost-crisis-how-government-policies-drive-consolidation-undermine-competition-and-fuel-soaring-prices/
34 Report to Congress: Overview of the 340B Drug Pricing Program. (2015). Medicare Payment Advisory Commission. https://www.medpac.gov/wp-content/uploads/import_data/scrape_files/docs/default-source/reports/may-2015-report-to-the-congress-overview-of-the-340b-drug-pricing-program.pdf
35 American Hospital Association v. Becerra, 596 U.S. 724 (2022). https://www.supremecourt.gov/docket/docketfiles/html/public/20-1114.html
36 Calendar Year 2027 Hospital Outpatient Prospective Payment System (OPPS) and Ambulatory Surgical Center (ASC) Proposed Rule (CMS-1850-P). (2026, July 2). Centers for Medicare & Medicaid Services. https://www.cms.gov/newsroom/fact-sheets/calendar-year-2027-hospital-outpatient-prospective-payment-system-opps-ambulatory-surgical-center
37 Centers for Medicare & Medicaid Services. "Medicare Program: Hospital Outpatient Prospective Payment and Ambulatory Surgical Center Payment Systems and Quality Reporting Programs." Federal Register, Vol. 88, No. 224, Nov. 22, 2023, pp. 81540–82185.
38 Health Resources & Services Administration. (n.d.). 340B Eligibility. Retrieved June 18, 2026, from https://www.hrsa.gov/opa/eligibility-and-registration
39 Notice Regarding Section 602 of the Veterans Health Care Act of 1992; Contract Pharmacy Services, 61 Fed. Reg. 43549-43556 (August 23, 1996). Federal Register Notice. https://www.federalregister.gov/documents/1996/08/23/96-21485/notice-regarding-section-602-of-the-veterans-health-care-act-of-1992-contract-pharmacy-services
40 Karen Mulligan, P. (2021). The 340B Drug Pricing Program: Background, Ongoing Challenges and Recent Developments. https://schaeffer.usc.edu/research/the-340b-drug-pricing-program-background-ongoing-challenges-and-recent-developments/
41 Notice Regarding 340B Drug Pricing Program-Contract Pharmacy Services, 75 Fed. Reg. 10272-10279 (March 5, 2010). https://www.federalregister.gov/documents/2010/03/05/2010-4755/notice-regarding-340b-drug-pricing-program-contract-pharmacy-services
42 Medicare Program: Hospital Outpatient Prospective Payment and Ambulatory Surgical Center Payment Systems and Quality Reporting Programs, 82 Fed. Reg. 52356-52637 (November 13, 2017). https://www.federalregister.gov/documents/2017/11/13/2017-23932/medicare-program-hospital-outpatient-prospective-payment-and-ambulatory-surgical-center-payment
43 Centers for Medicare & Medicaid Services. (2023, November 2). Hospital Outpatient Prospective Payment System (OPPS): Remedy for the 340B-Acquired Drug Payment Policy for Calendar Years 2018-2022 Final Rule (CMS 1793-F). https://www.cms.gov/newsroom/fact-sheets/hospital-outpatient-prospective-payment-system-opps-remedy-340b-acquired-drug-payment-policy
44 Overview of the 340B Drug Discount Program. (2026, June 18). https://www.congress.gov/crs-product/IF12232
45 Health Resources & Services Administration. (n.d.). 340B Administrative Dispute Resolution (ADR). Retrieved June 18, 2026, from https://www.hrsa.gov/opa/340b-administrative-dispute-resolution
46 Association of American Medical Colleges. (2024, April 19). HRSA Finalizes Revised 340B Administrative Dispute Resolution Process. https://www.aamc.org/advocacy-policy/washington-highlights/hrsa-finalizes-revised-340b-administrative-dispute-resolution-process
47 Health Resources & Services Administration. (2025, July 31). HRSA Announces Application Process for the 340B Rebate Model Pilot Program and Request for Public Comment. https://www.hrsa.gov/about/news/press-releases/rebate-model-pilot-program
48 Health Resources & Services Administration. (2026). 340B Rebate Model Pilot Program. https://www.hrsa.gov/opa/340b-model-pilot-program
49 Notice Regarding 340B Rebate Model Pilot Program, 91 F.R. 48883 (August 3, 2026). https://www.govinfo.gov/content/pkg/FR-2026-08-03/pdf/2026-15633.pdf
ABOUT THE AUTHORS
Aiden Lee is a Public Health Analyst in the Office of Health Policy in ASPE.
Khrysta A. Dunkel is an ORISE Fellow in the Office of Health Policy in ASPE.
Eden Volkov is an Economist in the Office of Health Policy in ASPE.
Sebastian Askar is an Advisor to the Chief Economist and Chief Regulatory Officer for Health and Human Services.
Casey B. Mulligan is the Chief Economist and Chief Regulatory Officer for Health and Human Services.
Ge Bai is the Principal Deputy Assistant Secretary for Planning and Evaluation in ASPE.
SUGGESTED CITATION
Lee, A., Dunkel, K.A., Volkov, E., Askar, S., Mulligan, C.B., Bai, G. Mission vs. Margin: Misaligned Incentives in the 340B Drug Pricing Program. Office of the Assistant Secretary for Planning and Evaluation, U.S. Department of Health and Human Services. October 2026.
COPYRIGHT INFORMATION
All material appearing in this report is in the public domain and may be reproduced or copied without permission; citation as to source, however, is appreciated.
DISCLOSURE
This communication was printed, published, or produced and disseminated at U.S. taxpayer expense.
Links and references to information from non-governmental organizations are provided for informational purposes and are not an HHS endorsement, recommendation, or preference for the non-governmental organizations.